- Home
- Best Foods for Diabetes and What to Avoid
- Can People With Type 2 Diabetes Eat Grapes and How Many
Grapes and Diabetes
If you live with diabetes, it is understandable to want a simple answer to the question, “What blood sugar should I aim for?”
For many adults, there are well-established treatment targets. However, I always remind my patients that these are general goals, not one-size-fits-all rules. Your safest target depends on your age, type and duration of diabetes, medicines, risk of hypoglycemia, pregnancy status, kidney or heart disease, and overall health.
The goal is not to keep glucose at one perfect number all day. It is to remain within a safe range as consistently as possible while avoiding prolonged high blood sugar and unnecessary low blood sugar.
Quick Answer: Common Blood Glucose Targets
For many nonpregnant adults with diabetes, commonly used treatment goals are:
- Before meals: 80–130 mg/dL (4.4–7.2 mmol/L)
- Peak after meals: below 180 mg/dL (below 10.0 mmol/L), measured 1–2 hours after the beginning of the meal
- A1C: below 7% (below 53 mmol/mol), when this can be achieved safely
| Measurement | Common target | What it means |
|---|---|---|
| Before meals | 80–130 mg/dL (4.4–7.2 mmol/L) |
A common premeal target for many nonpregnant adults |
| Peak after meals | Below 180 mg/dL (below 10.0 mmol/L) |
Usually assessed 1–2 hours after the beginning of the meal |
| A1C | Below 7% (below 53 mmol/mol) |
A common longer-term goal when it can be reached safely |
What Does “Acceptable Blood Glucose” Mean?
An acceptable blood glucose level is not necessarily the same as a “normal” glucose level in someone without diabetes.
When we set a diabetes target, we balance two priorities: keeping glucose low enough to reduce the risk of long-term complications while avoiding hypoglycemia and treatment that is too aggressive for the individual patient.
A single blood glucose reading does not provide a complete picture of diabetes control. In clinical practice, I consider the broader pattern, including fasting and premeal glucose levels, post-meal readings when appropriate, A1C, episodes of hypoglycemia, symptoms, current medications, and, when available, continuous glucose monitoring (CGM) data. These measures should also be interpreted in the context of established blood glucose and A1C ranges for normal glucose, prediabetes, and diabetes.
Acceptable Blood Glucose Before Meals
For many nonpregnant adults with diabetes, a common target before meals is 80–130 mg/dL (4.4–7.2 mmol/L).
This gives us useful information about your baseline glucose before food begins to raise it. If most of your premeal readings are within your agreed target, that is encouraging, but they should still be interpreted together with your post-meal pattern, A1C, low-glucose episodes and overall treatment plan.
A reading of 80 mg/dL is not hypoglycemia. It is near the lower end of the usual premeal target. Hypoglycemia is generally defined as glucose below 70 mg/dL.
If fasting or premeal readings are repeatedly above your personal target, possible contributors include overnight glucose production, meal or medication timing, illness, poor sleep, stress and changes in physical activity. A pattern over several days is more informative than one isolated morning reading.
If morning glucose is your main concern, see our guide to fasting blood sugar levels.
Acceptable Blood Glucose After Meals
For many adults with diabetes, a common target is a peak post-meal glucose below 180 mg/dL (10.0 mmol/L).
When post-meal glucose is being assessed, it is generally measured 1–2 hours after the beginning of the meal. The timing matters because this period is intended to capture glucose near its post-meal peak.
One reading slightly above 180 mg/dL does not necessarily mean your treatment is failing. A larger meal, more carbohydrate than usual, illness, stress, poor sleep or reduced activity can all affect the result. More important questions are whether higher readings occur frequently, remain elevated for a long time, or appear alongside an A1C or CGM pattern showing excessive glucose exposure.
Because blood glucose changes throughout the day, the timing of a measurement matters, particularly when interpreting blood sugar levels after eating.
How Does A1C Fit With Daily Blood Sugar Targets?
Daily readings show what your blood sugar is doing at a particular moment. A1C provides a broader view of glucose exposure over the previous two to three months, with more recent weeks contributing more to the result.
For many nonpregnant adults with diabetes, a common A1C goal is below 7% (53 mmol/mol) when it can be achieved safely. Some people may benefit from a lower goal. Others need a less stringent goal because hypoglycemia, frailty, serious comorbidities, cognitive or functional limitations, or treatment burden makes tighter control less safe.
I would not interpret A1C in isolation. Two people can have the same A1C while experiencing very different patterns of highs and lows.
Learn more in A1C vs Blood Sugar, or use our HbA1c to Average Glucose Calculator.
What If I Use a Continuous Glucose Monitor?
A continuous glucose monitor, or CGM, helps us look beyond individual fingerstick readings. It shows how much time glucose spends within, above and below the target range.
| CGM metric | Common goal for many adults |
|---|---|
| Time in range: 70–180 mg/dL | More than 70% of the time |
| Time below 70 mg/dL | Less than 4% of the time |
| Time below 54 mg/dL | Less than 1% of the time |
| Time above 180 mg/dL | Less than 25% of the time |
CGM goals also need to be individualized. Some older adults with complex health problems, for example, may need more permissive goals to reduce the risk of hypoglycemia.
What About Bedtime Blood Sugar?
There is no single bedtime glucose target appropriate for every adult with diabetes. Bedtime goals depend on insulin use, risk of overnight hypoglycemia, age, other medical conditions, recent exercise, meal timing and the treatment plan you follow.
If you use insulin or medicines that can cause hypoglycemia, your clinician may give you a specific bedtime target. Follow that individualized plan rather than relying on a universal bedtime number from the internet.
What Is Considered Low Blood Sugar?
For people with diabetes, glucose below 70 mg/dL (3.9 mmol/L) is considered hypoglycemia and should be taken seriously. A level below 54 mg/dL (3.0 mmol/L) is more clinically significant.
Symptoms may include shakiness, sweating, hunger, palpitations, dizziness, weakness, irritability, confusion or difficulty concentrating. If you have a hypoglycemia treatment plan, follow it promptly. Frequent low readings require medical review because medication dose, meal timing or activity may need adjustment.
Why Your Personal Target May Be Different
I would not give exactly the same glucose goal to every patient. Your targets may need to be individualized if you:
- are pregnant or planning pregnancy;
- are a child or adolescent;
- are an older adult;
- have frequent or severe hypoglycemia;
- have impaired awareness of low blood sugar;
- have significant kidney, heart, liver or other medical disease;
- have cognitive or functional limitations;
- have lived with diabetes for many years; or
- use insulin or medicines that increase hypoglycemia risk.
An older adult who is otherwise healthy may still have relatively tight glucose goals. Someone with frailty, several serious illnesses or recurrent hypoglycemia may need more relaxed targets because preventing low blood sugar becomes the greater priority.

What Can Affect Your Blood Glucose Readings?
Even when your treatment plan has not changed, glucose can vary from day to day. Common influences include:
- meal size and carbohydrate content;
- physical activity;
- stress and sleep;
- infection, illness or pain;
- dehydration or alcohol;
- hormonal changes;
- medication timing;
- missed insulin or diabetes medicine; and
- corticosteroids and some other medicines.
This is why I encourage patients to look for patterns rather than reacting strongly to one unusual result.

How to Keep Blood Glucose Closer to Your Target
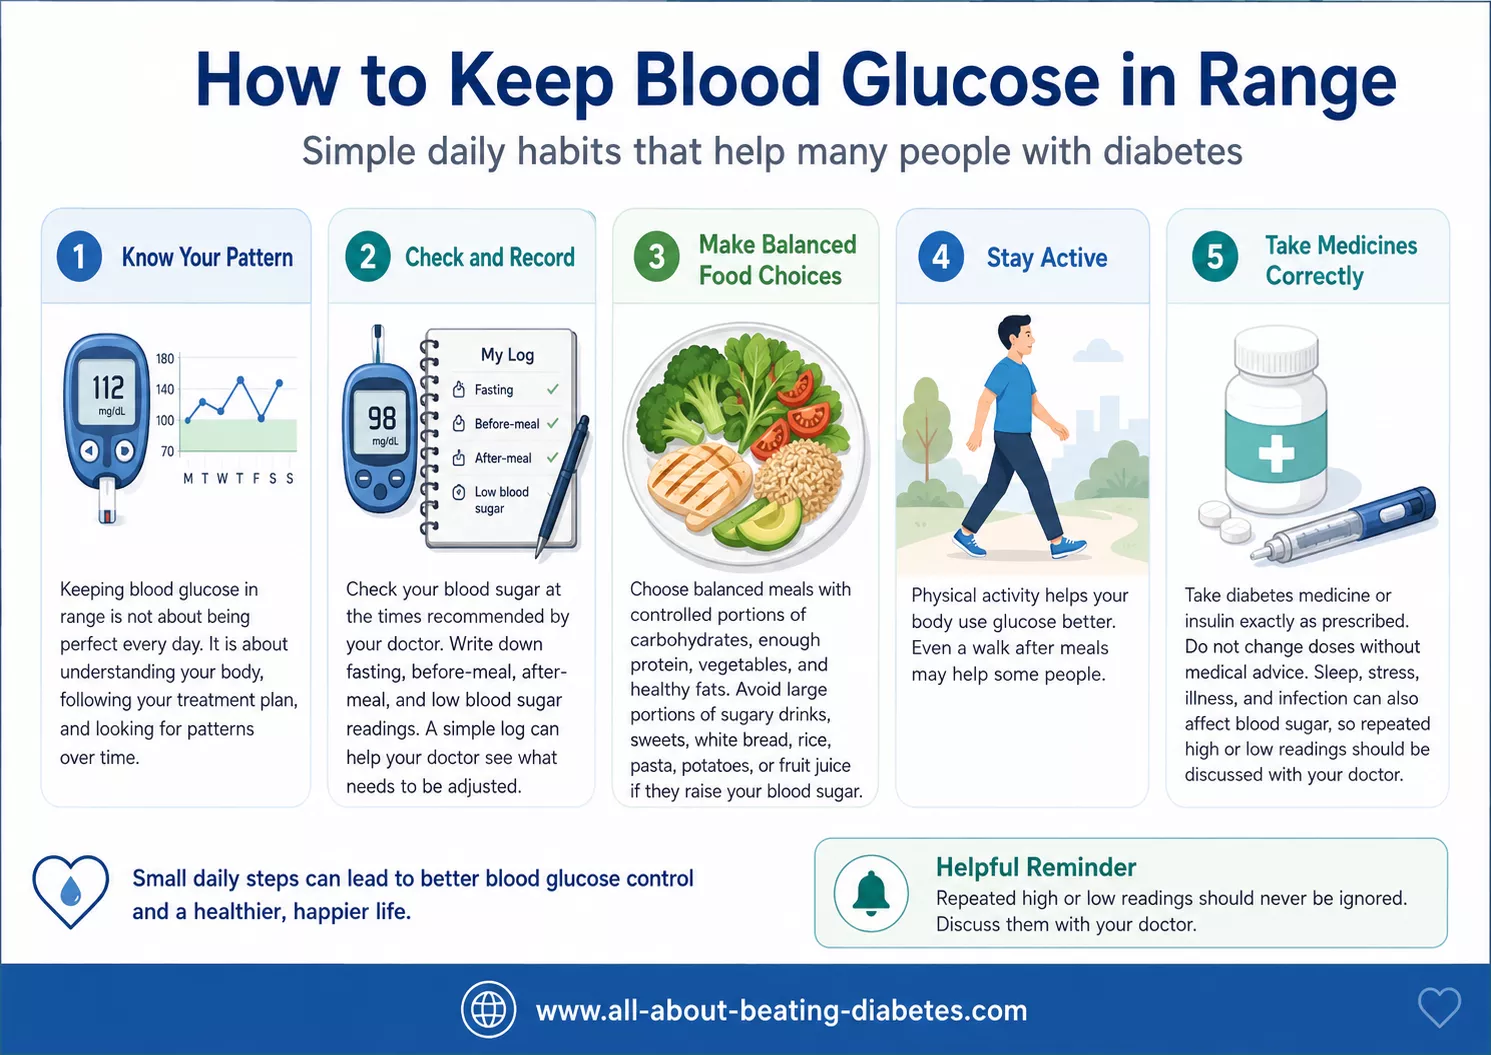
Keeping glucose in range does not require perfect numbers every day. The practical goal is to make the overall pattern safer and more consistent. Depending on your treatment plan, helpful steps may include:
- taking insulin or diabetes medicine exactly as prescribed;
- checking glucose at the times recommended by your healthcare team;
- keeping carbohydrate portions reasonably consistent when this is part of your plan;
- choosing meals with vegetables, protein, fiber and appropriate carbohydrate portions;
- being physically active regularly;
- reviewing repeated highs or lows instead of changing medication on your own;
- paying attention to sleep, illness, stress and hydration; and
- bringing your glucose log or CGM report to medical appointments.
Do not change insulin or medication doses because of one unusual result unless your healthcare professional has given you a specific adjustment plan.
Dr. Albana’s Perspective
When a patient asks whether a blood sugar number is “acceptable,” I first ask when it was measured and what target we agreed on for that person.
A premeal glucose of 125 mg/dL may be within the usual target for many adults with diabetes. The same number means something different if we are discussing a fasting laboratory test used to screen a person who has not been diagnosed with diabetes.
I also do not judge diabetes control from one good reading or one bad reading. I want to know whether most values are reasonably close to target, whether there are repeated highs, whether low glucose is occurring, and whether the A1C or CGM report tells the same story.
The best target is not the lowest number you can achieve. It is the range that offers meaningful long-term protection while remaining safe and realistic for your health and treatment.
When Should You Contact Your Doctor?
Contact your healthcare team if:
- glucose is repeatedly above your agreed target;
- you have repeated readings below 70 mg/dL;
- you experience nighttime hypoglycemia;
- your A1C is rising despite apparently reasonable daily readings;
- your CGM shows frequent highs or lows;
- you are ill and glucose becomes difficult to control;
- you are unsure whether medication or insulin needs adjustment; or
- your target may no longer be appropriate because of pregnancy, aging or a new medical condition.
Related Questions
Is 130 mg/dL acceptable for someone with diabetes?
It depends on when it was measured. For many nonpregnant adults, 130 mg/dL is at the upper end of the common premeal target. After a meal, it may also be within an acceptable range, but your individual target may differ.
Is 180 mg/dL after eating acceptable?
For many adults with diabetes, the common goal is a peak post-meal glucose below 180 mg/dL, assessed 1–2 hours after the beginning of the meal. Frequent readings at or above this level should be reviewed as a pattern.
Is 70 mg/dL acceptable?
Seventy mg/dL is the threshold at which we become concerned about hypoglycemia. A reading below 70 mg/dL should be treated according to your diabetes plan, and repeated lows should be discussed with your healthcare team.
Should everyone with diabetes have the same glucose target?
No. Age, pregnancy, medications, hypoglycemia risk, kidney or heart disease, functional status and other health conditions can all affect the safest goal.
What should my blood sugar be at bedtime?
There is no universal bedtime target for every adult with diabetes. Your bedtime goal should reflect your treatment plan, especially if you use insulin or are at risk of overnight hypoglycemia.
Is A1C below 7% right for everyone?
No. Below 7% is a common goal for many nonpregnant adults, but some people may benefit from a lower goal and others need a less stringent one for safety.
Related Tools and Calculators
Related Resources
Final Key Message
For many nonpregnant adults with diabetes, common treatment goals are 80–130 mg/dL before meals, below 180 mg/dL at the peak after meals, and A1C below 7% when these goals can be achieved safely.
If you use CGM, spending more than 70% of the time between 70 and 180 mg/dL is a common goal for many adults, while time below 70 mg/dL should remain limited.
Most importantly, your target should fit you. A safe plan balances glucose control with your risk of hypoglycemia, medications, age, other medical conditions and daily life. I would rather see a patient follow a realistic, individualized target safely and consistently than chase a “perfect” number that creates unnecessary risk.
References
- American Diabetes Association Professional Practice Committee. Glycemic Goals, Hypoglycemia, and Hyperglycemic Crises: Standards of Care in Diabetes—2026. Diabetes Care. 2026;49(Suppl. 1).
- American Diabetes Association Professional Practice Committee. Older Adults: Standards of Care in Diabetes—2026. Diabetes Care. 2026;49(Suppl. 1).
- American Diabetes Association. Checking Your Blood Sugar.
- National Institute of Diabetes and Digestive and Kidney Diseases. Managing Diabetes. National Institutes of Health.
Medical disclaimer: This information is for general education and does not replace professional medical advice, diagnosis or treatment. Follow the glucose targets and treatment plan recommended by your healthcare professional. Do not change insulin or diabetes medication doses without appropriate medical guidance.
If you enjoy grapes but worry that their sweetness will raise your blood sugar, you do not need to remove them automatically. I usually encourage my patients to focus on the portion, the total carbohydrate in the meal, and their own glucose pattern rather than judging fruit by sweetness alone.
Yes, most people with type 1 or type 2 diabetes can eat whole grapes. Grapes contain natural sugar and carbohydrate, so the amount still matters. About 17 grapes provide approximately 15 grams of carbohydrate in the American Diabetes Association’s serving example, although grape size and variety differ. A practical starting point is about ½ cup of whole grapes, counted as part of your meal or snack. Your personal portion may be different if you use insulin, have pregnancy-related targets, kidney disease, gastroparesis, or a prescribed meal plan.


Can People With Diabetes Eat Grapes?
Yes. Having diabetes does not mean that all sweet-tasting fruit must be avoided. Grapes are whole fruit and provide water, carbohydrate, small amounts of fiber, vitamins, minerals, and plant compounds called polyphenols. The American Diabetes Association includes grapes among fruit choices for people with diabetes.
However, grapes are easy to eat quickly and a large bunch can provide much more carbohydrate than expected. The useful question is not simply, “Are grapes allowed?” It is, “How much fits into my meal plan, and what happens to my glucose after I eat that amount?”
How Many Grapes Can a Person With Diabetes Eat?
The ADA Diabetes Food Hub lists 17 grapes as one serving with about 15 grams of total carbohydrate, 13 grams of naturally occurring sugar, 1 gram of fiber, and 60 calories. This is a useful reference—not a rule that every grape contains exactly the same amount.
Grapes differ greatly in size. Newer table-grape varieties can be much larger than traditional small grapes, so a count of 17 large grapes may provide more carbohydrate than 17 small grapes. For daily use, about ½ cup is a practical starting measure. If accurate carbohydrate counting is important for your mealtime insulin, use a food scale, a reliable nutrition database, or the package label when available.
| Form | Approximate 15-g carbohydrate reference | What to remember |
|---|---|---|
| Whole grapes | About 17 grapes in the ADA serving example; roughly ½ cup is a practical starting portion | Size and variety change the exact count. Measure your usual grapes. |
| Raisins | About 2 tablespoons | Drying concentrates the carbohydrate into a very small portion. |
| 100% fruit juice | Often about ⅓–½ cup, depending on the juice | Check the label. Juice is less filling and easier to drink quickly. |
Your dietitian may recommend more or less carbohydrate at a snack or meal. There is no universal grape limit for everyone with diabetes.
Do Grapes Raise Blood Sugar?
Yes. The natural glucose and fructose in grapes are carbohydrates, and digestible carbohydrate can raise blood glucose. The size of the rise depends on the portion, your diabetes type, insulin production and sensitivity, medicine or insulin timing, activity, the rest of the meal, time of day, and your individual digestion.
Grapes are often described as having a low average glycemic index, but GI values vary by grape variety, ripeness, testing method, and portion. A low or moderate GI does not mean the food has no carbohydrate or that an unlimited portion will have a small effect. Total carbohydrate and the amount you actually eat remain important.
Learn how total carbohydrate, glycemic index, and glycemic load affect blood sugar. You can also compare your result with the guidance on blood sugar levels after eating.
How to check your personal response
- Measure a repeatable portion. Start with about ½ cup or the amount in your meal plan.
- Record the complete snack or meal. Include other carbohydrate, protein, fat, medicine, insulin, and activity.
- Check at the times your diabetes team recommends. Many people compare the reading before eating with a reading 1–2 hours after the start of the meal, but your instructions may differ.
- Look for a pattern. One result can be changed by sleep, stress, illness, exercise, or medicine timing. Repeat a similar comparison before drawing a conclusion.
Do not change insulin or diabetes medicine based on one food experiment. If your readings are repeatedly outside your personal target, share the pattern with your diabetes team.
Are Red, Green, or Black Grapes Better for Diabetes?
No grape color has been proven to control diabetes better than another. Red and dark-purple grapes often contain more visible anthocyanin pigments, while all grape colors contain plant compounds. These differences do not make carbohydrate disappear and have not established a clinically superior grape color for blood-sugar treatment.
What matters more
- The portion you actually eat
- Total carbohydrate in the meal
- Whole fruit versus juice or dried fruit
- Your repeated meter or CGM response
What matters less
- Whether the grapes are red, green, or black
- Whether they are seedless or seeded
- Whether they taste slightly sweeter or tarter
- Unproven “superfruit” marketing claims
Choose the color and variety you enjoy, then measure the serving. If one variety is unusually large, use volume or weight instead of relying on grape count.
Whole Grapes, Grape Juice, or Raisins?
For an everyday fruit choice, whole grapes usually make portion control easier than grape juice or raisins. Whole grapes retain their water and structure, so the serving occupies more space and takes longer to eat.
- Whole grapes: usually the most practical everyday choice when measured.
- Frozen grapes: have essentially the same carbohydrate as fresh grapes; freezing does not remove sugar.
- Raisins: are dried grapes, so the carbohydrate is concentrated. Two tablespoons can provide about 15 grams.
- Grape juice: can provide 15 grams of carbohydrate in a small amount and is easy to drink quickly. Read the serving label.
- Wine: is not a fruit serving. Alcohol has separate safety concerns and may increase hypoglycemia risk in people using insulin or certain medicines.
Juice can have a role in a written hypoglycemia plan because it is a fast source of carbohydrate. For routine meals and snacks, whole fruit is generally more filling. If you take an alpha-glucosidase inhibitor such as acarbose and develop hypoglycemia, use glucose tablets or gel as instructed because other carbohydrate sources may act too slowly.
What Is the Best Way to Eat Grapes With Diabetes?
You can eat grapes as the fruit portion of a balanced meal or as a measured snack. Pairing them with a suitable protein or unsaturated-fat food may increase fullness and may change the timing of your glucose response, but it does not cancel the carbohydrate in the grapes.
- About ½ cup grapes with plain unsweetened Greek yogurt
- A measured grape portion with a small amount of nuts
- Grapes in a salad with leafy vegetables and a protein source
- Grapes as the fruit portion alongside a balanced meal
Avoid turning a small fruit serving into a high-carbohydrate snack by adding sweetened yogurt, honey, syrup, granola, dried fruit, or a large amount of crackers without counting those foods too.
Grapes, Type 1 Diabetes, and Mealtime Insulin
People with type 1 diabetes can eat grapes, but their carbohydrate should be included in the mealtime or snack calculation according to the personal insulin-to-carbohydrate ratio provided by the diabetes team. Do not calculate insulin from the grape’s GI or copy another person’s dose.
Because grape size varies, weighing the edible portion can be more accurate than counting individual grapes. If grapes are eaten with fat or protein, the glucose response may be delayed; this can matter for insulin timing, pumps, and people with gastroparesis. Insulin adjustments should follow your own written plan.
Do Grapes, Resveratrol, or Polyphenols Treat Diabetes?
No. Grapes contain polyphenols, including anthocyanins, flavonoids, and small amounts of resveratrol. These compounds are scientifically interesting, but eating grapes has not been established as a treatment that lowers HbA1c, reverses diabetes, protects pancreatic cells, or prevents diabetes complications.
Laboratory findings, animal studies, observational associations, and small supplement trials cannot be translated into a promise that a serving of grapes will lower your blood sugar. Whole grapes can be included because they are a nutritious fruit—not because they work like diabetes medicine.
I also do not recommend grape-seed extract, resveratrol capsules, or concentrated grape products as substitutes for prescribed treatment. Supplements can have different doses and safety profiles from whole food and may interact with medicines.
Special Situations
Pregnancy and gestational diabetes
Fruit can fit during pregnancy, but glucose targets are tighter and carbohydrate may need to be distributed carefully across the day. Follow your pregnancy meal plan and monitoring instructions rather than using a general serving as your personal target.
Kidney disease
The ADA serving example for 17 grapes lists about 160 mg potassium. Many people with kidney disease can include a measured portion, but potassium, fluid, and carbohydrate goals vary by kidney function, dialysis, laboratory results, and medicines. Follow your renal dietitian’s advice.
Gastroparesis
Grape skins and fiber may be difficult for some people with delayed stomach emptying. Food texture, portion size, and insulin timing may need individual adjustment.
Children and swallowing difficulty
Whole grapes are a choking hazard for young children and for anyone with swallowing problems. Cut grapes lengthwise into small pieces and follow age-appropriate or clinician-provided swallowing guidance.
Food safety
Wash grapes under clean running water just before eating. Do not wash them with soap or household detergent. Discard grapes that are moldy or spoiled.
Doctor’s Note
Frequently Asked Questions About Grapes and Diabetes
Can a person with type 2 diabetes eat grapes every day?
They may be able to, provided the portion fits their overall carbohydrate and nutrition plan. Variety in fruit choices is still useful, and repeated glucose results can help show whether the portion works for that person.
How many grapes equal 15 grams of carbohydrate?
The ADA Diabetes Food Hub uses 17 grapes as a serving with 15 grams of carbohydrate. Because grape sizes vary, this is an approximate guide. Volume, weight, or package information may be more accurate for large varieties.
Is half a cup of grapes too much for diabetes?
For many people, about half a cup is a reasonable starting fruit portion. Your needs may differ based on insulin, medicines, pregnancy, kidney health, activity, and the carbohydrate in the rest of the meal.
Which grapes have the least sugar: red, green, or black?
Carbohydrate varies by variety and ripeness, but no color is reliably “free” of sugar or clearly best for diabetes. Portion size matters more than choosing grapes by color.
Are seedless grapes worse for blood sugar?
No consistent evidence shows that seedless grapes are inherently worse. Compare the portion and carbohydrate content; some seedless varieties are very large, which can make grape counts misleading.
Are frozen grapes good for diabetes?
Frozen whole grapes can fit, but freezing does not reduce their carbohydrate. Measure the portion before or after freezing and be careful if hard frozen foods are difficult for you to chew.
Are raisins as good as fresh grapes?
Raisins contain many of the same grape compounds, but drying removes water and concentrates the carbohydrate. A 15-gram carbohydrate portion is only about two tablespoons, so raisins are easier to overeat and may be less filling.
Can grapes lower blood sugar or HbA1c?
Grapes are not a glucose-lowering treatment. They contain carbohydrate and generally raise blood sugar after eating. Their polyphenols are being studied, but grapes should not replace medication, nutrition therapy, physical activity, or monitoring.
Should I eat grapes to treat low blood sugar?
Whole grapes contain carbohydrate, but they are difficult to measure quickly and are not usually the most predictable first choice. Follow your written hypoglycemia plan, which commonly uses 15–20 grams of fast-acting carbohydrate such as glucose tablets, glucose gel, or measured juice. If you cannot swallow safely, someone should use glucagon if available and call emergency services.
Related Questions From Readers
- Which glycemic-index fruits can I eat with diabetes?
- Do people with diabetes need strict food restrictions?
- Which foods are better for prediabetes?
- Is a low-carbohydrate diet safe for type 2 diabetes?
Related Resources
- Diabetes Foods, Fruit, and Blood Sugar
- Low-Glycemic-Index Fruits
- Glycemic Index Chart
- Glycemic Load Chart and Calculator
- Carbohydrate Counter
- Blood Sugar Levels After Eating
- Diabetes-Friendly Cooking and Recipes
- Carbohydrates, GI, and Diabetes
References
- American Diabetes Association Diabetes Food Hub. 17 Grapes: Serving and Nutrition Facts.
- American Diabetes Association. Best Fruit Choices for Diabetes.
- American Diabetes Association Professional Practice Committee. Facilitating Positive Health Behaviors and Well-being: Standards of Care in Diabetes—2026.
- National Institute of Diabetes and Digestive and Kidney Diseases. Healthy Living With Diabetes.
- U.S. Department of Agriculture. FoodData Central.
- Zunino SJ. Type 2 Diabetes and Glycemic Response to Grapes or Grape Products. Journal of Nutrition. 2009.
- National Institute of Diabetes and Digestive and Kidney Diseases. Low Blood Glucose (Hypoglycemia).