“Is my blood sugar normal?”
Timing matters. A fasting reading, a result before dinner, and a reading two hours after eating can mean very different things.
Understand Your Blood Sugar →If you live with diabetes, it is understandable to want a simple answer to the question, “What blood sugar should I aim for?”
For many adults, there are well-established treatment targets. However, I always remind my patients that these are general goals, not one-size-fits-all rules. Your safest target depends on your age, type and duration of diabetes, medicines, risk of hypoglycemia, pregnancy status, kidney or heart disease, and overall health.
The goal is not to keep glucose at one perfect number all day. It is to remain within a safe range as consistently as possible while avoiding prolonged high blood sugar and unnecessary low blood sugar.
For many nonpregnant adults with diabetes, commonly used treatment goals are:
| Measurement | Common target | What it means |
|---|---|---|
| Before meals | 80–130 mg/dL (4.4–7.2 mmol/L) |
A common premeal target for many nonpregnant adults |
| Peak after meals | Below 180 mg/dL (below 10.0 mmol/L) |
Usually assessed 1–2 hours after the beginning of the meal |
| A1C | Below 7% (below 53 mmol/mol) |
A common longer-term goal when it can be reached safely |
An acceptable blood glucose level is not necessarily the same as a “normal” glucose level in someone without diabetes.
When we set a diabetes target, we balance two priorities: keeping glucose low enough to reduce the risk of long-term complications while avoiding hypoglycemia and treatment that is too aggressive for the individual patient.
A single blood glucose reading does not provide a complete picture of diabetes control. In clinical practice, I consider the broader pattern, including fasting and premeal glucose levels, post-meal readings when appropriate, A1C, episodes of hypoglycemia, symptoms, current medications, and, when available, continuous glucose monitoring (CGM) data. These measures should also be interpreted in the context of established blood glucose and A1C ranges for normal glucose, prediabetes, and diabetes.
For many nonpregnant adults with diabetes, a common target before meals is 80–130 mg/dL (4.4–7.2 mmol/L).
This gives us useful information about your baseline glucose before food begins to raise it. If most of your premeal readings are within your agreed target, that is encouraging, but they should still be interpreted together with your post-meal pattern, A1C, low-glucose episodes and overall treatment plan.
A reading of 80 mg/dL is not hypoglycemia. It is near the lower end of the usual premeal target. Hypoglycemia is generally defined as glucose below 70 mg/dL.
If fasting or premeal readings are repeatedly above your personal target, possible contributors include overnight glucose production, meal or medication timing, illness, poor sleep, stress and changes in physical activity. A pattern over several days is more informative than one isolated morning reading.
If morning glucose is your main concern, see our guide to fasting blood sugar levels.
For many adults with diabetes, a common target is a peak post-meal glucose below 180 mg/dL (10.0 mmol/L).
When post-meal glucose is being assessed, it is generally measured 1–2 hours after the beginning of the meal. The timing matters because this period is intended to capture glucose near its post-meal peak.
One reading slightly above 180 mg/dL does not necessarily mean your treatment is failing. A larger meal, more carbohydrate than usual, illness, stress, poor sleep or reduced activity can all affect the result. More important questions are whether higher readings occur frequently, remain elevated for a long time, or appear alongside an A1C or CGM pattern showing excessive glucose exposure.
Because blood glucose changes throughout the day, the timing of a measurement matters, particularly when interpreting blood sugar levels after eating.
Daily readings show what your blood sugar is doing at a particular moment. A1C provides a broader view of glucose exposure over the previous two to three months, with more recent weeks contributing more to the result.
For many nonpregnant adults with diabetes, a common A1C goal is below 7% (53 mmol/mol) when it can be achieved safely. Some people may benefit from a lower goal. Others need a less stringent goal because hypoglycemia, frailty, serious comorbidities, cognitive or functional limitations, or treatment burden makes tighter control less safe.
I would not interpret A1C in isolation. Two people can have the same A1C while experiencing very different patterns of highs and lows.
Learn more in A1C vs Blood Sugar, or use our HbA1c to Average Glucose Calculator.
A continuous glucose monitor, or CGM, helps us look beyond individual fingerstick readings. It shows how much time glucose spends within, above and below the target range.
| CGM metric | Common goal for many adults |
|---|---|
| Time in range: 70–180 mg/dL | More than 70% of the time |
| Time below 70 mg/dL | Less than 4% of the time |
| Time below 54 mg/dL | Less than 1% of the time |
| Time above 180 mg/dL | Less than 25% of the time |
CGM goals also need to be individualized. Some older adults with complex health problems, for example, may need more permissive goals to reduce the risk of hypoglycemia.
There is no single bedtime glucose target appropriate for every adult with diabetes. Bedtime goals depend on insulin use, risk of overnight hypoglycemia, age, other medical conditions, recent exercise, meal timing and the treatment plan you follow.
If you use insulin or medicines that can cause hypoglycemia, your clinician may give you a specific bedtime target. Follow that individualized plan rather than relying on a universal bedtime number from the internet.
For people with diabetes, glucose below 70 mg/dL (3.9 mmol/L) is considered hypoglycemia and should be taken seriously. A level below 54 mg/dL (3.0 mmol/L) is more clinically significant.
Symptoms may include shakiness, sweating, hunger, palpitations, dizziness, weakness, irritability, confusion or difficulty concentrating. If you have a hypoglycemia treatment plan, follow it promptly. Frequent low readings require medical review because medication dose, meal timing or activity may need adjustment.
I would not give exactly the same glucose goal to every patient. Your targets may need to be individualized if you:
An older adult who is otherwise healthy may still have relatively tight glucose goals. Someone with frailty, several serious illnesses or recurrent hypoglycemia may need more relaxed targets because preventing low blood sugar becomes the greater priority.

Even when your treatment plan has not changed, glucose can vary from day to day. Common influences include:
This is why I encourage patients to look for patterns rather than reacting strongly to one unusual result.

Keeping glucose in range does not require perfect numbers every day. The practical goal is to make the overall pattern safer and more consistent. Depending on your treatment plan, helpful steps may include:
Do not change insulin or medication doses because of one unusual result unless your healthcare professional has given you a specific adjustment plan.
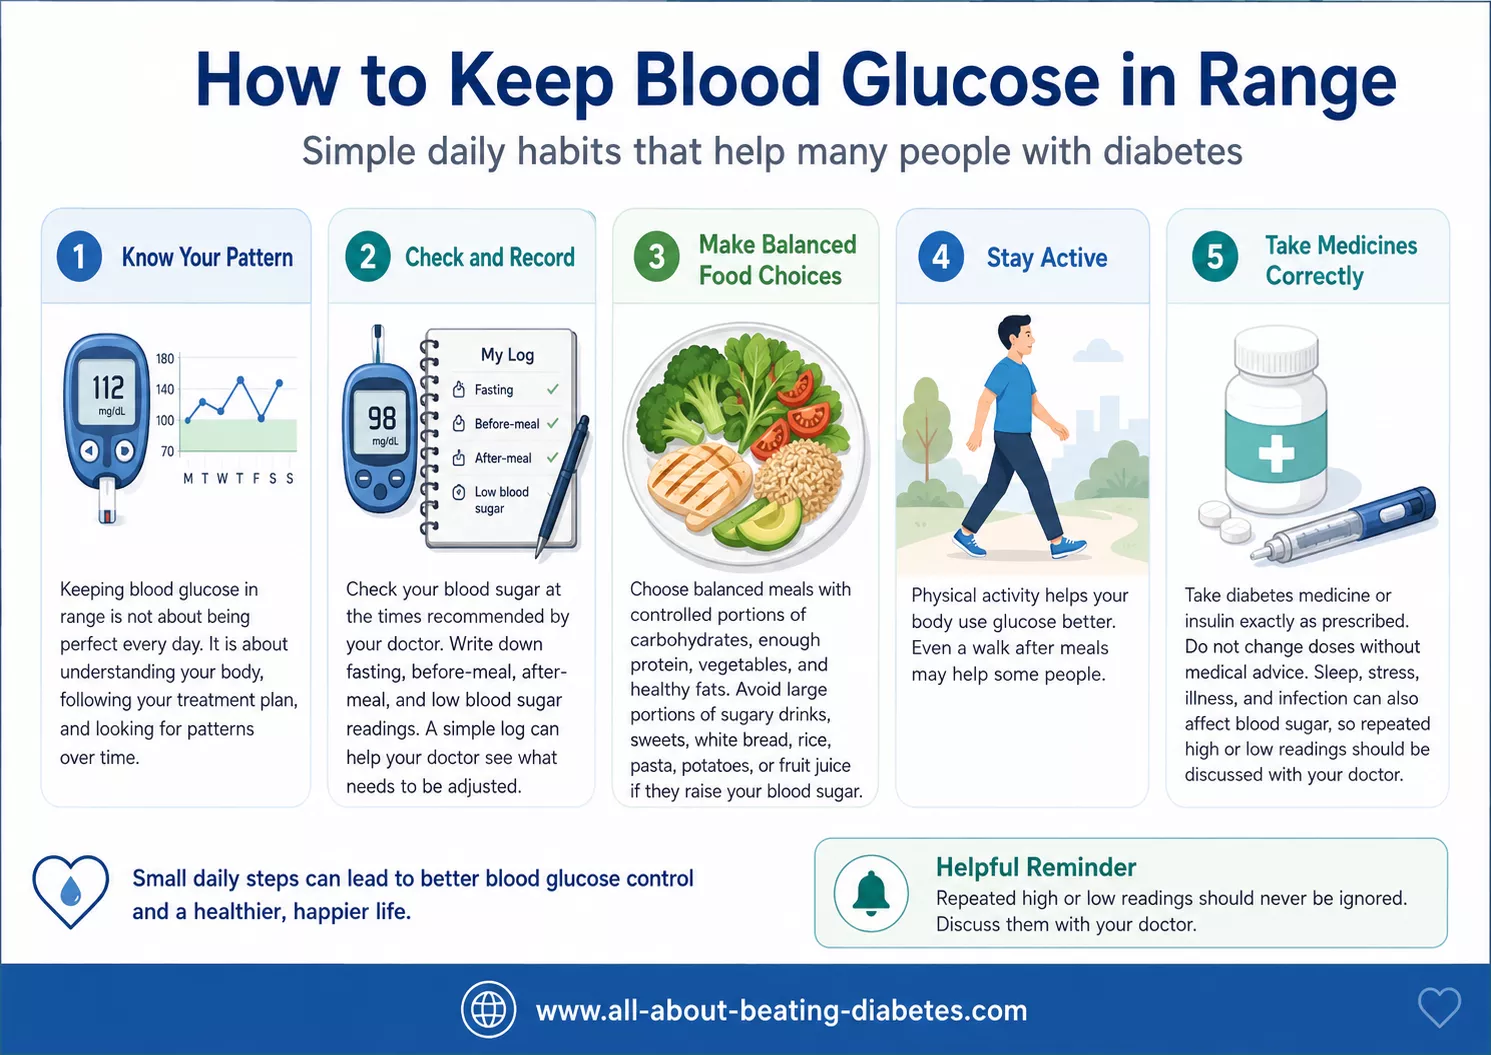
When a patient asks whether a blood sugar number is “acceptable,” I first ask when it was measured and what target we agreed on for that person.
A premeal glucose of 125 mg/dL may be within the usual target for many adults with diabetes. The same number means something different if we are discussing a fasting laboratory test used to screen a person who has not been diagnosed with diabetes.
I also do not judge diabetes control from one good reading or one bad reading. I want to know whether most values are reasonably close to target, whether there are repeated highs, whether low glucose is occurring, and whether the A1C or CGM report tells the same story.
The best target is not the lowest number you can achieve. It is the range that offers meaningful long-term protection while remaining safe and realistic for your health and treatment.
Contact your healthcare team if:
It depends on when it was measured. For many nonpregnant adults, 130 mg/dL is at the upper end of the common premeal target. After a meal, it may also be within an acceptable range, but your individual target may differ.
For many adults with diabetes, the common goal is a peak post-meal glucose below 180 mg/dL, assessed 1–2 hours after the beginning of the meal. Frequent readings at or above this level should be reviewed as a pattern.
Seventy mg/dL is the threshold at which we become concerned about hypoglycemia. A reading below 70 mg/dL should be treated according to your diabetes plan, and repeated lows should be discussed with your healthcare team.
No. Age, pregnancy, medications, hypoglycemia risk, kidney or heart disease, functional status and other health conditions can all affect the safest goal.
There is no universal bedtime target for every adult with diabetes. Your bedtime goal should reflect your treatment plan, especially if you use insulin or are at risk of overnight hypoglycemia.
No. Below 7% is a common goal for many nonpregnant adults, but some people may benefit from a lower goal and others need a less stringent one for safety.
For many nonpregnant adults with diabetes, common treatment goals are 80–130 mg/dL before meals, below 180 mg/dL at the peak after meals, and A1C below 7% when these goals can be achieved safely.
If you use CGM, spending more than 70% of the time between 70 and 180 mg/dL is a common goal for many adults, while time below 70 mg/dL should remain limited.
Most importantly, your target should fit you. A safe plan balances glucose control with your risk of hypoglycemia, medications, age, other medical conditions and daily life. I would rather see a patient follow a realistic, individualized target safely and consistently than chase a “perfect” number that creates unnecessary risk.
Medical disclaimer: This information is for general education and does not replace professional medical advice, diagnosis or treatment. Follow the glucose targets and treatment plan recommended by your healthcare professional. Do not change insulin or diabetes medication doses without appropriate medical guidance.
Doctor-Led Diabetes Education
If you came here because a blood sugar number frightened you, your HbA1c changed, you are unsure what to eat, or your treatment has changed, start with the question that matters most to you today.
“I created Beating Diabetes to explain these questions the same way I explain them to my patients: clearly, practically, and without making diabetes more frightening than it already feels.”
— Dr. Albana Greca, MD, MMedSc , Family Physician
Start With Your Immediate Question
Most people do not arrive at a diabetes website wanting to read everything. Choose the concern that sounds most like yours.
Timing matters. A fasting reading, a result before dinner, and a reading two hours after eating can mean very different things.
Understand Your Blood Sugar →HbA1c tells a broader story than one fasting glucose reading and should be interpreted together with your daily pattern and health history.
Understand HbA1c →Diabetes does not automatically mean giving up bread, rice, fruit, or every food you enjoy. Portions, combinations, and your own glucose response matter.
Explore Food Choices →Needing metformin, insulin, a GLP-1 medicine, or another treatment does not mean you have failed. Diabetes often changes over time.
Understand Diabetes Medicines →A Simple Starting Path
If you are newly diagnosed—or simply trying to make sense of your results—do not try to learn everything at once.
Learn how timing changes the meaning of a glucose result.
Start with blood sugar →Understand long-term glucose exposure and how HbA1c differs from a single reading.
Learn about HbA1c →Work with your numbers before discussing them with your healthcare professional.
Open the calculators →Explore by Topic
Fasting, before-meal, after-meal, high, low, and potentially dangerous glucose ranges.
Explore Blood Sugar →What HbA1c measures, how it relates to average glucose, and how targets differ from diagnosis.
Explore HbA1c →How fasting glucose, HbA1c, OGTT, and home monitoring differ.
Explore Testing →Understand risk, glucose and insulin patterns, and what deserves attention first.
Explore Insulin Resistance →Carbohydrates, portions, meal balance, and practical food choices without unnecessary fear.
Explore Diabetes Food →Why different medicines are used, how treatment changes, and which safety issues matter.
Explore Medications →How diabetes can affect the eyes, kidneys, nerves, feet, heart, and blood vessels.
Explore Complications →Common Patient Questions
These are the questions people ask when they are worried about a real number, symptom, meal, or treatment decision.
Work With Your Numbers
These educational tools can help you understand common measurements before you discuss them with your healthcare professional.
Medical Trust & Transparency
Medical content is written or supervised by qualified physicians and is reviewed by relevant specialists when a page requires additional clinical expertise.
Founder, Lead Medical Author & Family Physician
Leads the site's medical-education standards and writes or supervises patient-focused diabetes content.
Endocrinologist & Specialist Medical Reviewer
Provides specialist review for diabetes, insulin resistance, metabolic disease, nutrition, and endocrine topics when appropriate.
Transparency: A doctor is listed as a medical reviewer only after reviewing the relevant version of that page.
A Practical Perspective
Diabetes care is not about producing one “perfect” glucose number. It is about understanding patterns, reducing avoidable risk, and making treatment decisions that you can realistically live with.
A good plan should help protect your eyes, kidneys, nerves, feet, heart, and blood vessels while also protecting you from hypoglycemia, unnecessary restriction, and treatment that is too difficult to maintain.
Some days your numbers will be better than others. What matters most is the pattern, the reason behind it, and what you do next.
— Dr. Albana Greca
Our Medical Team
Different medical topics may benefit from different clinical perspectives. Our team brings experience in family medicine, endocrinology, cardiology, and gastroenterology.
Family Physician • Founder • Lead Medical Author
Patient-focused diabetes education, primary care, glucose interpretation, HbA1c, medications, prevention and chronic-disease management.
Endocrinologist • Specialist Medical Reviewer
Diabetes, insulin resistance, endocrine disease, metabolic health, obesity and clinical nutrition.
Cardiologist • Medical Contributor
Cardiovascular risk, blood pressure, cholesterol, circulation, heart disease and diabetes-related cardiovascular health.
Gastroenterologist • Medical Contributor
Digestive health, liver disease, gastrointestinal symptoms, nutrition and metabolic conditions connected with diabetes.
Keep Learning
Get new diabetes guides, blood sugar explanations, calculators, and Q&A answers from Dr. Albana Greca.
Get diabetes updates by email, RSS, or Telegram →All About Beating Diabetes provides general medical education and is not a substitute for diagnosis, emergency care, or individualized treatment from your own clinician. Do not start, stop, increase, decrease, or otherwise change insulin or another prescription medicine solely from information on this Website.