- Home
- blood sugar levels
- Dangerous levels
What Blood Sugar Level Is Dangerous?
Learn when high or low blood sugar may require urgent or emergency medical care.
Written by: Dr. Albana Greca Sejdini, MD, MMedSc • Medically reviewed by: Dr. Ruden Cakoni, MD, Endocrinologist Last medically reviewed: August 2026
One of the most common questions patients ask me is, “At what blood sugar level should I become worried?” It is an important question, but there is not one glucose number that separates safe from dangerous in every person.
Very low glucose can interfere with brain function, while very high glucose can lead to severe dehydration and medical emergencies such as diabetic ketoacidosis (DKA) or hyperosmolar hyperglycemic state (HHS). I therefore look at the glucose number together with symptoms, ketones, illness, medications, hydration and how quickly the level is changing.
If you are trying to understand an ordinary reading rather than an emergency, start with our normal blood sugar level chart or compare your result with our blood sugar levels by time of day. This page focuses specifically on readings and symptoms that may require urgent action.
Quick Answer
A glucose level below 70 mg/dL (3.9 mmol/L) is low and should be treated promptly. A level below 54 mg/dL (3.0 mmol/L) is clinically significant hypoglycemia. Severe hypoglycemia becomes an emergency when a person cannot safely treat themselves, regardless of the exact glucose number.
There is no single high-glucose number that defines every emergency. Persistent readings around 250–300 mg/dL deserve attention, especially during illness or when ketones or symptoms are present. Readings above 400 mg/dL are extremely high and need prompt assessment if they do not improve or serious symptoms occur.
A glucose of 600 mg/dL (33.3 mmol/L) or higher is one criterion used when doctors evaluate for HHS. However, DKA can occur at much lower glucose levels, sometimes even below 200 mg/dL.
When to Seek Emergency Care
When blood sugar is abnormal, I do not want my patients to watch only the meter. Certain symptoms tell us that the brain, circulation, hydration or body's acid-base balance may already be affected.
This is especially important with diabetic ketoacidosis, severe hypoglycemia and HHS. If severe warning signs are present, do not keep waiting for the glucose to reach a particular number.
Seek emergency medical care immediately if a person develops:
- confusion, fainting, severe drowsiness or difficulty waking
- seizure or loss of consciousness
- repeated vomiting or inability to keep fluids down
- rapid, deep or difficult breathing
- fruity-smelling breath together with other DKA symptoms
- severe dehydration or rapidly worsening weakness
- significant ketones together with illness or DKA symptoms
- very high glucose that does not improve according to the prescribed treatment plan
- severe hypoglycemia when the person cannot safely treat themselves
Chest pain, severe shortness of breath, face drooping, arm weakness, trouble speaking or other signs of heart attack or stroke also require emergency care regardless of the glucose reading.
Blood Sugar Levels That Need Attention
The following chart helps you understand how different glucose levels are generally interpreted. It is deliberately not called a “safe versus dangerous” chart, because the same glucose value may have a different meaning depending on symptoms, timing, illness, ketones and whether you already have diabetes.
For comparison, ordinary fasting and after-meal readings are explained separately in our normal fasting blood sugar guide and blood sugar after eating chart. The ranges below focus on levels requiring increased attention.
| Glucose | mmol/L | What it may mean | General action |
|---|---|---|---|
| <54 mg/dL | <3.0 | Level 2, clinically significant hypoglycemia | Treat immediately; get help if the person cannot safely self-treat |
| 54–69 mg/dL | 3.0–3.8 | Level 1 hypoglycemia | Treat promptly and recheck |
| >180 mg/dL | >10.0 | Above the usual post-meal target for many adults with diabetes | Look at the pattern; repeated highs may require treatment review |
| About 250–300 mg/dL | 13.9–16.7 | Very high; more concerning with illness, missed insulin, dehydration or ketones | Follow your sick-day/correction plan and seek advice if it persists or symptoms occur |
| >400 mg/dL | >22.2 | Extremely high glucose with increased risk of dehydration and metabolic deterioration | Prompt medical advice; emergency evaluation if significant symptoms or ketones occur |
| ≥600 mg/dL | ≥33.3 | Meets the glucose criterion used when evaluating for HHS | Urgent hospital evaluation is required |
The key message is that you should not wait for glucose to reach 300, 400 or 600 mg/dL when serious symptoms are already present. DKA can occur at substantially lower glucose levels, and severe hypoglycemia is determined partly by the person's ability to function and treat themselves.
Blood Sugar Safety Checker
Many patients naturally want to enter a glucose number and receive a simple answer. A checker can help show whether the reading falls into a low, usual, high or very high range, but it cannot determine whether someone is medically safe from the glucose number alone.
Before using any calculator or checker, remember that the timing of the reading matters. A result before breakfast is interpreted differently from one taken after lunch. Our blood sugar levels by time of day guide explains these differences in more detail.
When High Blood Sugar Becomes Concerning
High blood sugar, or hyperglycemia, may cause thirst, frequent urination, fatigue and blurred vision. When glucose remains very high, the kidneys try to remove excess glucose through urine. Water is lost with it, which can gradually lead to dehydration.
A single high reading does not always mean an emergency. It is the combination of how high the glucose is, how long it stays high, symptoms and the reason it is rising that determines the level of concern. For ordinary after-meal elevations, see our guide to high blood sugar after eating.
Blood Sugar Around 250–300 mg/dL
A glucose level around 250–300 mg/dL (13.9–16.7 mmol/L) is very high. It does not automatically mean that DKA is present, but it deserves attention—particularly in people with type 1 diabetes, during illness, after missed insulin or when ketones are present.
Warning symptoms that make the situation more urgent include:
- extreme thirst and frequent urination
- nausea or vomiting
- abdominal pain
- unusual fatigue
- rapid or deep breathing
- worsening dehydration
- confusion or unusual drowsiness
If you use insulin, follow the sick-day and correction instructions given by your own diabetes team. Do not improvise repeated correction doses. Our insulin bolus and correction calculator is an educational tool for people who already know their prescribed correction factor; it is not an emergency-treatment calculator.
Blood Sugar Above 400 mg/dL
A confirmed glucose above 400 mg/dL (22.2 mmol/L) is extremely high. At this level, dehydration can worsen quickly, especially if the person is urinating frequently, vomiting, unable to drink normally or fighting an infection.
Seek urgent medical assessment when very high glucose does not improve according to your prescribed plan or occurs with ketones, vomiting, abdominal pain, rapid/deep breathing, severe dehydration, confusion or extreme drowsiness.
Dangerous Low Blood Sugar: Hypoglycemia
Low blood sugar deserves special attention because the brain depends heavily on glucose. A person may initially feel hungry, shaky or sweaty, but as glucose falls further, thinking, coordination and consciousness can become impaired.
If you want a more detailed explanation of these numbers, see our guides to blood sugar between 45 and 69 mg/dL and blood sugar below 54 mg/dL.
Current diabetes guidance divides hypoglycemia into three clinically useful levels:
| Level | Definition | Why it matters |
|---|---|---|
| Level 1 | Below 70 but at least 54 mg/dL | Low glucose requiring prompt treatment |
| Level 2 | Below 54 mg/dL (3.0 mmol/L) | Clinically significant hypoglycemia requiring immediate action |
| Level 3 | Severe event requiring another person's assistance | Medical emergency defined by severity, not a specific glucose number |
Repeated episodes of low glucose should not simply be accepted as part of diabetes treatment. Our page on causes of low blood glucose explains how insulin, medications, meals, exercise, alcohol, kidney function and other factors may contribute.
How to Treat Low Blood Sugar
If glucose is below 70 mg/dL and the person is awake and able to swallow safely, the goal is to raise glucose promptly with fast-acting carbohydrate and then confirm that it has recovered.
A commonly used approach for most adults is the 15–15 rule:
- Take about 15 grams of fast-acting carbohydrate.
- Recheck glucose after 15 minutes.
- If it remains low, repeat treatment.
- Once glucose recovers, follow your healthcare professional's advice about food if the next meal is not soon.
Medical Emergencies Linked to Blood Sugar
Very abnormal glucose can lead to several different medical emergencies, and they do not all occur at the same glucose level. Understanding the difference between DKA, HHS and severe hypoglycemia helps explain why symptoms sometimes matter more than the meter reading.
These conditions require medical evaluation because treatment involves much more than lowering or raising glucose. Doctors may also need to correct dehydration, electrolyte problems, ketones and abnormal acidity and identify the illness or treatment problem that triggered the emergency.
Diabetic Ketoacidosis (DKA)
Diabetic ketoacidosis occurs when the body does not have enough effective insulin. The body begins breaking down fat for energy, producing ketones that can accumulate and make the blood too acidic.
Common warning signs include nausea, repeated vomiting, abdominal pain, fruity-smelling breath, rapid/deep breathing, extreme fatigue, dehydration and confusion.
This is particularly important during illness, pregnancy, prolonged fasting and with SGLT2 inhibitor medicines. For a fuller explanation, read diabetic ketoacidosis symptoms, causes and emergency treatment.
Hyperosmolar Hyperglycemic State (HHS)
Hyperosmolar hyperglycemic state usually develops differently from DKA. Glucose becomes extremely high, large amounts of water are lost through the urine, and severe dehydration and hyperosmolarity develop.
Possible signs include extreme thirst, frequent urination, dry mouth, marked weakness, confusion, increasing drowsiness, seizures and loss of consciousness.
A plasma glucose of 600 mg/dL (33.3 mmol/L) or higher is one criterion used when doctors evaluate for HHS, but glucose alone does not establish the diagnosis. Suspected HHS requires immediate hospital evaluation.
Diabetic Coma
The term diabetic coma describes severe loss of consciousness related to a diabetes emergency rather than one particular glucose level. It can occur with severe hypoglycemia, DKA, HHS or another serious medical problem.
If someone with diabetes becomes extremely drowsy, confused, unresponsive, has a seizure or loses consciousness, do not wait for another glucose reading. Call emergency services. You can read more about diabetic coma warning signs and causes.
What Are Ketones, and Why Do They Matter?
Ketones are produced when the body uses fat for energy. Small amounts may occur during fasting or reduced carbohydrate intake, so detecting any ketones does not automatically mean that someone has DKA.
In a person with diabetes, however, moderate or high urine ketones or significantly elevated blood ketones become more concerning when they occur with illness, missed insulin, persistent hyperglycemia or symptoms such as vomiting and abdominal pain.
If you are at risk for DKA, your sick-day plan should explain when and how to check ketones. Do not wait for glucose to become extremely high if DKA symptoms are developing.
What to Do When Blood Sugar Is Very High
If glucose is very high but you are awake, able to drink normally and do not have emergency symptoms, the first step is to follow the plan already provided by your diabetes team rather than improvising additional medication.
- recheck an unexpected meter reading when appropriate
- drink water unless fluid intake has been medically restricted
- follow your personal sick-day and correction plan
- check ketones when advised
- avoid strenuous exercise when significant ketones are present
- contact your healthcare professional if glucose or ketones do not improve
Never repeatedly take extra insulin unless this is part of a correction plan prescribed specifically for you.
When Should You Go to the Hospital?
Patients sometimes delay seeking help because they are waiting for a particular number to appear on the meter. I would rather you judge an emergency by the whole clinical situation.
Inability to drink, repeated vomiting, abnormal breathing, significant ketones and changes in consciousness may signal serious metabolic illness even when the glucose is below a number you expected to be “dangerous.”
Seek emergency assessment for:
- repeated vomiting or inability to keep fluids down
- abdominal pain together with other DKA symptoms
- rapid, deep or difficult breathing
- confusion, severe drowsiness or difficulty waking
- significant ketones or very high glucose that do not improve
- glucose around or above 600 mg/dL
- seizure or loss of consciousness
- severe hypoglycemia that prevents the person from treating themselves
Do not delay emergency care because glucose appears “not high enough.” Symptoms and the person's overall condition can be more important than the number alone.
Why Dangerous Blood Sugar Levels Happen
A glucose emergency usually has a cause. Finding that trigger matters because simply correcting the glucose without addressing the underlying problem can allow the situation to happen again.
High glucose may be related to illness, infection, missed insulin, steroid medicines, dehydration or progression of diabetes. Low glucose may follow excessive insulin, certain diabetes medicines, skipped meals, alcohol or unexpected physical activity.
- missed insulin or diabetes medication
- infection, fever or another illness
- dehydration
- vomiting or poor food intake
- prolonged fasting or skipped meals
- too much insulin or another glucose-lowering medicine
- sulfonylurea treatment combined with inadequate food intake
- alcohol use
- stress, surgery or serious inflammation
- incorrect insulin dose or timing
If low readings are the problem, see why blood glucose can become too low. If your concern is repeated morning highs rather than an acute emergency, our guide to high blood sugar in the morning explains dawn phenomenon, sleep, medication timing and other common causes.
Preventing Blood Sugar Emergencies
Not every diabetes emergency can be prevented, but preparation can greatly reduce risk. I encourage my patients to create a plan for both high and low glucose before they become ill or find themselves dealing with an unexpected reading.
A useful emergency plan should cover glucose monitoring, medication, meals and fluids, ketone testing, hypoglycemia treatment and when another person or medical team should become involved.
- monitor glucose as recommended and watch for unusual patterns
- take insulin and diabetes medicines at the prescribed dose and time
- stay adequately hydrated
- have a written sick-day plan
- know when and how to check ketones
- keep fast-acting glucose available if you are at risk for hypoglycemia
- have prescribed glucagon available when appropriate
- teach family members or caregivers how to respond to severe hypoglycemia
- know which symptoms require urgent or emergency care
For routine glucose management outside an emergency, see our blood sugar control guide.
Doctor's Note
When patients ask me, “What blood sugar number is dangerous?” I explain that I never look at the glucose value alone. I look at the number, symptoms, ketones, illness, medications, hydration and the direction glucose is moving. A very abnormal glucose deserves attention, but waiting for a particular number before asking for help can also be dangerous. If you are vomiting, confused, severely dehydrated, having difficulty breathing, having a seizure or unable to safely treat yourself, seek urgent medical care.
Most Asked Questions
These are some of the questions patients most often ask after seeing a glucose reading much higher or lower than expected. Each answer describes a general level of concern; symptoms and your personal diabetes plan can change what you should do.
Is 250 mg/dL dangerous?
A glucose of 250 mg/dL (13.9 mmol/L) is very high but is not automatically an emergency by itself. It becomes more concerning if it persists, occurs during illness, follows missed insulin or is accompanied by ketones, vomiting, abdominal pain, dehydration or breathing changes.
Is 300 mg/dL dangerous?
A glucose around 300 mg/dL (16.7 mmol/L) is very high and needs attention. Follow your prescribed sick-day or correction plan and seek medical advice if it does not improve. DKA symptoms, significant ketones, dehydration or confusion require urgent assessment.
Is 400 mg/dL dangerous?
A glucose around 400 mg/dL (22.2 mmol/L) is extremely high and warrants prompt attention. Emergency evaluation is especially important if it does not improve or occurs with ketones, vomiting, dehydration, confusion or breathing difficulty.
Is 600 mg/dL always HHS?
No. A plasma glucose of 600 mg/dL or higher is one diagnostic criterion for HHS, but additional laboratory findings are required. A glucose at this level nevertheless warrants urgent hospital evaluation.
Can DKA happen below 250 mg/dL?
Yes. DKA can occur around 200 mg/dL and sometimes below 200 mg/dL. This is especially important with SGLT2 inhibitors, pregnancy, prolonged fasting and certain illnesses.
What blood sugar is dangerously low?
Glucose below 54 mg/dL (3.0 mmol/L) is clinically significant Level 2 hypoglycemia. Severe Level 3 hypoglycemia is defined by needing another person's assistance, regardless of the glucose number.
Can dangerous blood sugar occur without symptoms?
Yes. Some people have limited warning symptoms even when glucose is very high or low. Monitoring is particularly important for people taking insulin or medicines that can cause hypoglycemia.
Related Questions
For more detail about specific glucose situations and emergencies, these pages expand on the topics discussed above:
- Low Blood Sugar 45–69 mg/dL: Symptoms and What to Do
- Blood Sugar Below 54 mg/dL: Clinically Significant Hypoglycemia
- Diabetic Ketoacidosis: Symptoms, Causes and Emergency Treatment
- Diabetic Coma: Warning Signs and Causes
- Low Blood Glucose Causes
Related Resources
If your glucose is not currently in an emergency range, these broader guides can help you understand everyday readings and patterns:
- Normal Blood Sugar Level Chart
- Normal Fasting Blood Sugar Levels
- Blood Sugar Levels by Time of Day
- Blood Sugar Levels After Eating
- Convert mmol/L to mg/dL
Educational Safety Note
This article is designed to help you recognize potentially dangerous glucose patterns and understand when professional or emergency medical assessment may be needed. It does not diagnose DKA, HHS, hypoglycemia or another medical emergency.
Glucose readings should be interpreted together with symptoms, ketones, medications, illness, hydration and your individual diabetes plan. Do not take repeated extra doses of insulin or change diabetes medication because of information on this page unless your healthcare professional has given you specific instructions.
References
The medical thresholds and emergency guidance on this page are based primarily on current diabetes standards and clinical guidance on hypoglycemia and hyperglycemic emergencies.
- American Diabetes Association Professional Practice Committee. Glycemic Goals, Hypoglycemia, and Hyperglycemic Crises: Standards of Care in Diabetes—2026.
- American Diabetes Association Professional Practice Committee. Diabetes Care in the Hospital: Standards of Care in Diabetes—2026.
- Umpierrez GE, et al. Hyperglycemic Crises in Adults With Diabetes: A Consensus Report.
- National Institute of Diabetes and Digestive and Kidney Diseases. Low Blood Glucose (Hypoglycemia).
If you live with diabetes, it is understandable to want a simple answer to the question, “What blood sugar should I aim for?”
For many adults, there are well-established treatment targets. However, I always remind my patients that these are general goals, not one-size-fits-all rules. Your safest target depends on your age, type and duration of diabetes, medicines, risk of hypoglycemia, pregnancy status, kidney or heart disease, and overall health.
The goal is not to keep glucose at one perfect number all day. It is to remain within a safe range as consistently as possible while avoiding prolonged high blood sugar and unnecessary low blood sugar.
Quick Answer: Common Blood Glucose Targets
For many nonpregnant adults with diabetes, commonly used treatment goals are:
- Before meals: 80–130 mg/dL (4.4–7.2 mmol/L)
- Peak after meals: below 180 mg/dL (below 10.0 mmol/L), measured 1–2 hours after the beginning of the meal
- A1C: below 7% (below 53 mmol/mol), when this can be achieved safely
| Measurement | Common target | What it means |
|---|---|---|
| Before meals | 80–130 mg/dL (4.4–7.2 mmol/L) |
A common premeal target for many nonpregnant adults |
| Peak after meals | Below 180 mg/dL (below 10.0 mmol/L) |
Usually assessed 1–2 hours after the beginning of the meal |
| A1C | Below 7% (below 53 mmol/mol) |
A common longer-term goal when it can be reached safely |
What Does “Acceptable Blood Glucose” Mean?
An acceptable blood glucose level is not necessarily the same as a “normal” glucose level in someone without diabetes.
When we set a diabetes target, we balance two priorities: keeping glucose low enough to reduce the risk of long-term complications while avoiding hypoglycemia and treatment that is too aggressive for the individual patient.
A single blood glucose reading does not provide a complete picture of diabetes control. In clinical practice, I consider the broader pattern, including fasting and premeal glucose levels, post-meal readings when appropriate, A1C, episodes of hypoglycemia, symptoms, current medications, and, when available, continuous glucose monitoring (CGM) data. These measures should also be interpreted in the context of established blood glucose and A1C ranges for normal glucose, prediabetes, and diabetes.
Acceptable Blood Glucose Before Meals
For many nonpregnant adults with diabetes, a common target before meals is 80–130 mg/dL (4.4–7.2 mmol/L).
This gives us useful information about your baseline glucose before food begins to raise it. If most of your premeal readings are within your agreed target, that is encouraging, but they should still be interpreted together with your post-meal pattern, A1C, low-glucose episodes and overall treatment plan.
A reading of 80 mg/dL is not hypoglycemia. It is near the lower end of the usual premeal target. Hypoglycemia is generally defined as glucose below 70 mg/dL.
If fasting or premeal readings are repeatedly above your personal target, possible contributors include overnight glucose production, meal or medication timing, illness, poor sleep, stress and changes in physical activity. A pattern over several days is more informative than one isolated morning reading.
If morning glucose is your main concern, see our guide to fasting blood sugar levels.
Acceptable Blood Glucose After Meals
For many adults with diabetes, a common target is a peak post-meal glucose below 180 mg/dL (10.0 mmol/L).
When post-meal glucose is being assessed, it is generally measured 1–2 hours after the beginning of the meal. The timing matters because this period is intended to capture glucose near its post-meal peak.
One reading slightly above 180 mg/dL does not necessarily mean your treatment is failing. A larger meal, more carbohydrate than usual, illness, stress, poor sleep or reduced activity can all affect the result. More important questions are whether higher readings occur frequently, remain elevated for a long time, or appear alongside an A1C or CGM pattern showing excessive glucose exposure.
Because blood glucose changes throughout the day, the timing of a measurement matters, particularly when interpreting blood sugar levels after eating.
How Does A1C Fit With Daily Blood Sugar Targets?
Daily readings show what your blood sugar is doing at a particular moment. A1C provides a broader view of glucose exposure over the previous two to three months, with more recent weeks contributing more to the result.
For many nonpregnant adults with diabetes, a common A1C goal is below 7% (53 mmol/mol) when it can be achieved safely. Some people may benefit from a lower goal. Others need a less stringent goal because hypoglycemia, frailty, serious comorbidities, cognitive or functional limitations, or treatment burden makes tighter control less safe.
I would not interpret A1C in isolation. Two people can have the same A1C while experiencing very different patterns of highs and lows.
Learn more in A1C vs Blood Sugar, or use our HbA1c to Average Glucose Calculator.
What If I Use a Continuous Glucose Monitor?
A continuous glucose monitor, or CGM, helps us look beyond individual fingerstick readings. It shows how much time glucose spends within, above and below the target range.
| CGM metric | Common goal for many adults |
|---|---|
| Time in range: 70–180 mg/dL | More than 70% of the time |
| Time below 70 mg/dL | Less than 4% of the time |
| Time below 54 mg/dL | Less than 1% of the time |
| Time above 180 mg/dL | Less than 25% of the time |
CGM goals also need to be individualized. Some older adults with complex health problems, for example, may need more permissive goals to reduce the risk of hypoglycemia.
What About Bedtime Blood Sugar?
There is no single bedtime glucose target appropriate for every adult with diabetes. Bedtime goals depend on insulin use, risk of overnight hypoglycemia, age, other medical conditions, recent exercise, meal timing and the treatment plan you follow.
If you use insulin or medicines that can cause hypoglycemia, your clinician may give you a specific bedtime target. Follow that individualized plan rather than relying on a universal bedtime number from the internet.
What Is Considered Low Blood Sugar?
For people with diabetes, glucose below 70 mg/dL (3.9 mmol/L) is considered hypoglycemia and should be taken seriously. A level below 54 mg/dL (3.0 mmol/L) is more clinically significant.
Symptoms may include shakiness, sweating, hunger, palpitations, dizziness, weakness, irritability, confusion or difficulty concentrating. If you have a hypoglycemia treatment plan, follow it promptly. Frequent low readings require medical review because medication dose, meal timing or activity may need adjustment.
Why Your Personal Target May Be Different
I would not give exactly the same glucose goal to every patient. Your targets may need to be individualized if you:
- are pregnant or planning pregnancy;
- are a child or adolescent;
- are an older adult;
- have frequent or severe hypoglycemia;
- have impaired awareness of low blood sugar;
- have significant kidney, heart, liver or other medical disease;
- have cognitive or functional limitations;
- have lived with diabetes for many years; or
- use insulin or medicines that increase hypoglycemia risk.
An older adult who is otherwise healthy may still have relatively tight glucose goals. Someone with frailty, several serious illnesses or recurrent hypoglycemia may need more relaxed targets because preventing low blood sugar becomes the greater priority.

What Can Affect Your Blood Glucose Readings?
Even when your treatment plan has not changed, glucose can vary from day to day. Common influences include:
- meal size and carbohydrate content;
- physical activity;
- stress and sleep;
- infection, illness or pain;
- dehydration or alcohol;
- hormonal changes;
- medication timing;
- missed insulin or diabetes medicine; and
- corticosteroids and some other medicines.
This is why I encourage patients to look for patterns rather than reacting strongly to one unusual result.

How to Keep Blood Glucose Closer to Your Target
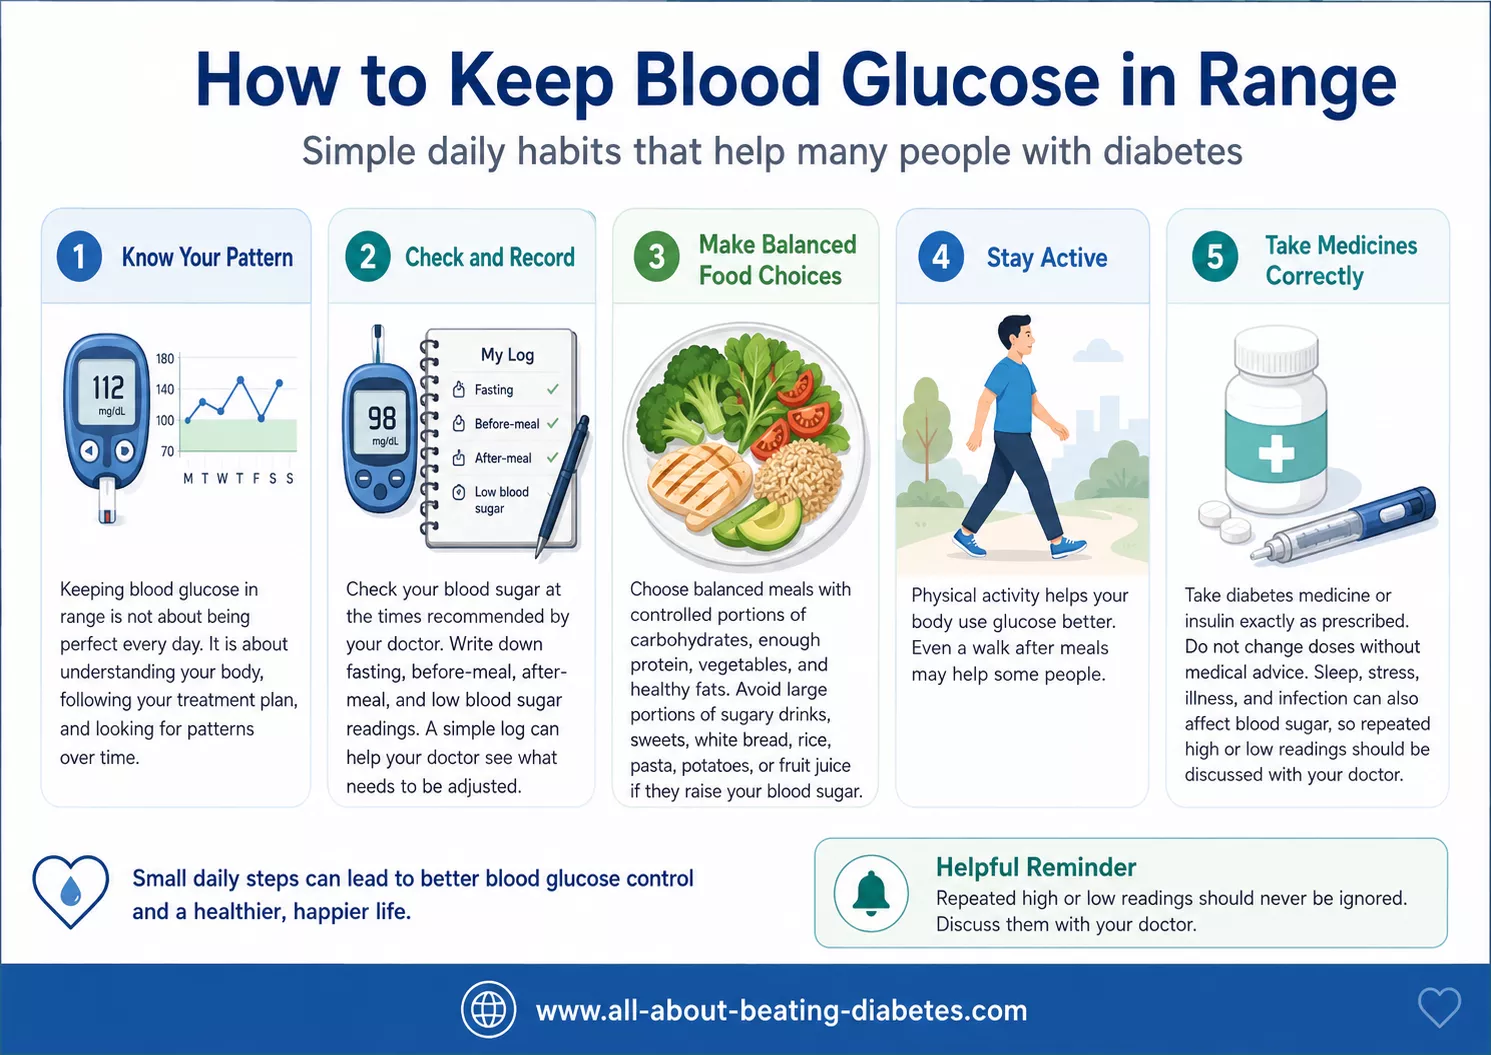
Keeping glucose in range does not require perfect numbers every day. The practical goal is to make the overall pattern safer and more consistent. Depending on your treatment plan, helpful steps may include:
- taking insulin or diabetes medicine exactly as prescribed;
- checking glucose at the times recommended by your healthcare team;
- keeping carbohydrate portions reasonably consistent when this is part of your plan;
- choosing meals with vegetables, protein, fiber and appropriate carbohydrate portions;
- being physically active regularly;
- reviewing repeated highs or lows instead of changing medication on your own;
- paying attention to sleep, illness, stress and hydration; and
- bringing your glucose log or CGM report to medical appointments.
Do not change insulin or medication doses because of one unusual result unless your healthcare professional has given you a specific adjustment plan.
Dr. Albana’s Perspective
When a patient asks whether a blood sugar number is “acceptable,” I first ask when it was measured and what target we agreed on for that person.
A premeal glucose of 125 mg/dL may be within the usual target for many adults with diabetes. The same number means something different if we are discussing a fasting laboratory test used to screen a person who has not been diagnosed with diabetes.
I also do not judge diabetes control from one good reading or one bad reading. I want to know whether most values are reasonably close to target, whether there are repeated highs, whether low glucose is occurring, and whether the A1C or CGM report tells the same story.
The best target is not the lowest number you can achieve. It is the range that offers meaningful long-term protection while remaining safe and realistic for your health and treatment.
When Should You Contact Your Doctor?
Contact your healthcare team if:
- glucose is repeatedly above your agreed target;
- you have repeated readings below 70 mg/dL;
- you experience nighttime hypoglycemia;
- your A1C is rising despite apparently reasonable daily readings;
- your CGM shows frequent highs or lows;
- you are ill and glucose becomes difficult to control;
- you are unsure whether medication or insulin needs adjustment; or
- your target may no longer be appropriate because of pregnancy, aging or a new medical condition.
Related Questions
Is 130 mg/dL acceptable for someone with diabetes?
It depends on when it was measured. For many nonpregnant adults, 130 mg/dL is at the upper end of the common premeal target. After a meal, it may also be within an acceptable range, but your individual target may differ.
Is 180 mg/dL after eating acceptable?
For many adults with diabetes, the common goal is a peak post-meal glucose below 180 mg/dL, assessed 1–2 hours after the beginning of the meal. Frequent readings at or above this level should be reviewed as a pattern.
Is 70 mg/dL acceptable?
Seventy mg/dL is the threshold at which we become concerned about hypoglycemia. A reading below 70 mg/dL should be treated according to your diabetes plan, and repeated lows should be discussed with your healthcare team.
Should everyone with diabetes have the same glucose target?
No. Age, pregnancy, medications, hypoglycemia risk, kidney or heart disease, functional status and other health conditions can all affect the safest goal.
What should my blood sugar be at bedtime?
There is no universal bedtime target for every adult with diabetes. Your bedtime goal should reflect your treatment plan, especially if you use insulin or are at risk of overnight hypoglycemia.
Is A1C below 7% right for everyone?
No. Below 7% is a common goal for many nonpregnant adults, but some people may benefit from a lower goal and others need a less stringent one for safety.
Related Tools and Calculators
Related Resources
Final Key Message
For many nonpregnant adults with diabetes, common treatment goals are 80–130 mg/dL before meals, below 180 mg/dL at the peak after meals, and A1C below 7% when these goals can be achieved safely.
If you use CGM, spending more than 70% of the time between 70 and 180 mg/dL is a common goal for many adults, while time below 70 mg/dL should remain limited.
Most importantly, your target should fit you. A safe plan balances glucose control with your risk of hypoglycemia, medications, age, other medical conditions and daily life. I would rather see a patient follow a realistic, individualized target safely and consistently than chase a “perfect” number that creates unnecessary risk.
References
- American Diabetes Association Professional Practice Committee. Glycemic Goals, Hypoglycemia, and Hyperglycemic Crises: Standards of Care in Diabetes—2026. Diabetes Care. 2026;49(Suppl. 1).
- American Diabetes Association Professional Practice Committee. Older Adults: Standards of Care in Diabetes—2026. Diabetes Care. 2026;49(Suppl. 1).
- American Diabetes Association. Checking Your Blood Sugar.
- National Institute of Diabetes and Digestive and Kidney Diseases. Managing Diabetes. National Institutes of Health.
Medical disclaimer: This information is for general education and does not replace professional medical advice, diagnosis or treatment. Follow the glucose targets and treatment plan recommended by your healthcare professional. Do not change insulin or diabetes medication doses without appropriate medical guidance.